
At a Glance
| Property | Value |
|---|---|
| Name | Peptide Therapy for Gut Healing |
| Peptides discussed | BPC-157, KPV, LL-37 |
| Route | Subcutaneous injection, Oral, IV |
| Typical Dose | 200-500 mcg |
| Evidence Level | Preclinical (peptides); stronger for diet and some supplements |
| Regulatory Status | None approved; all three FDA-flagged as compounding safety risks |
| Key Uses | A phased gut healing framework built on diagnosis, diet, and evidence-based supplements, with an honest look at gut peptides |
Key Takeaways:
- The gut has the strongest preclinical rationale for peptides, with animal data for multiple peptides, but no controlled human trials
- BPC-157 peptide therapy originated from gastric juice research and has extensive animal data for gastrointestinal protection and healing
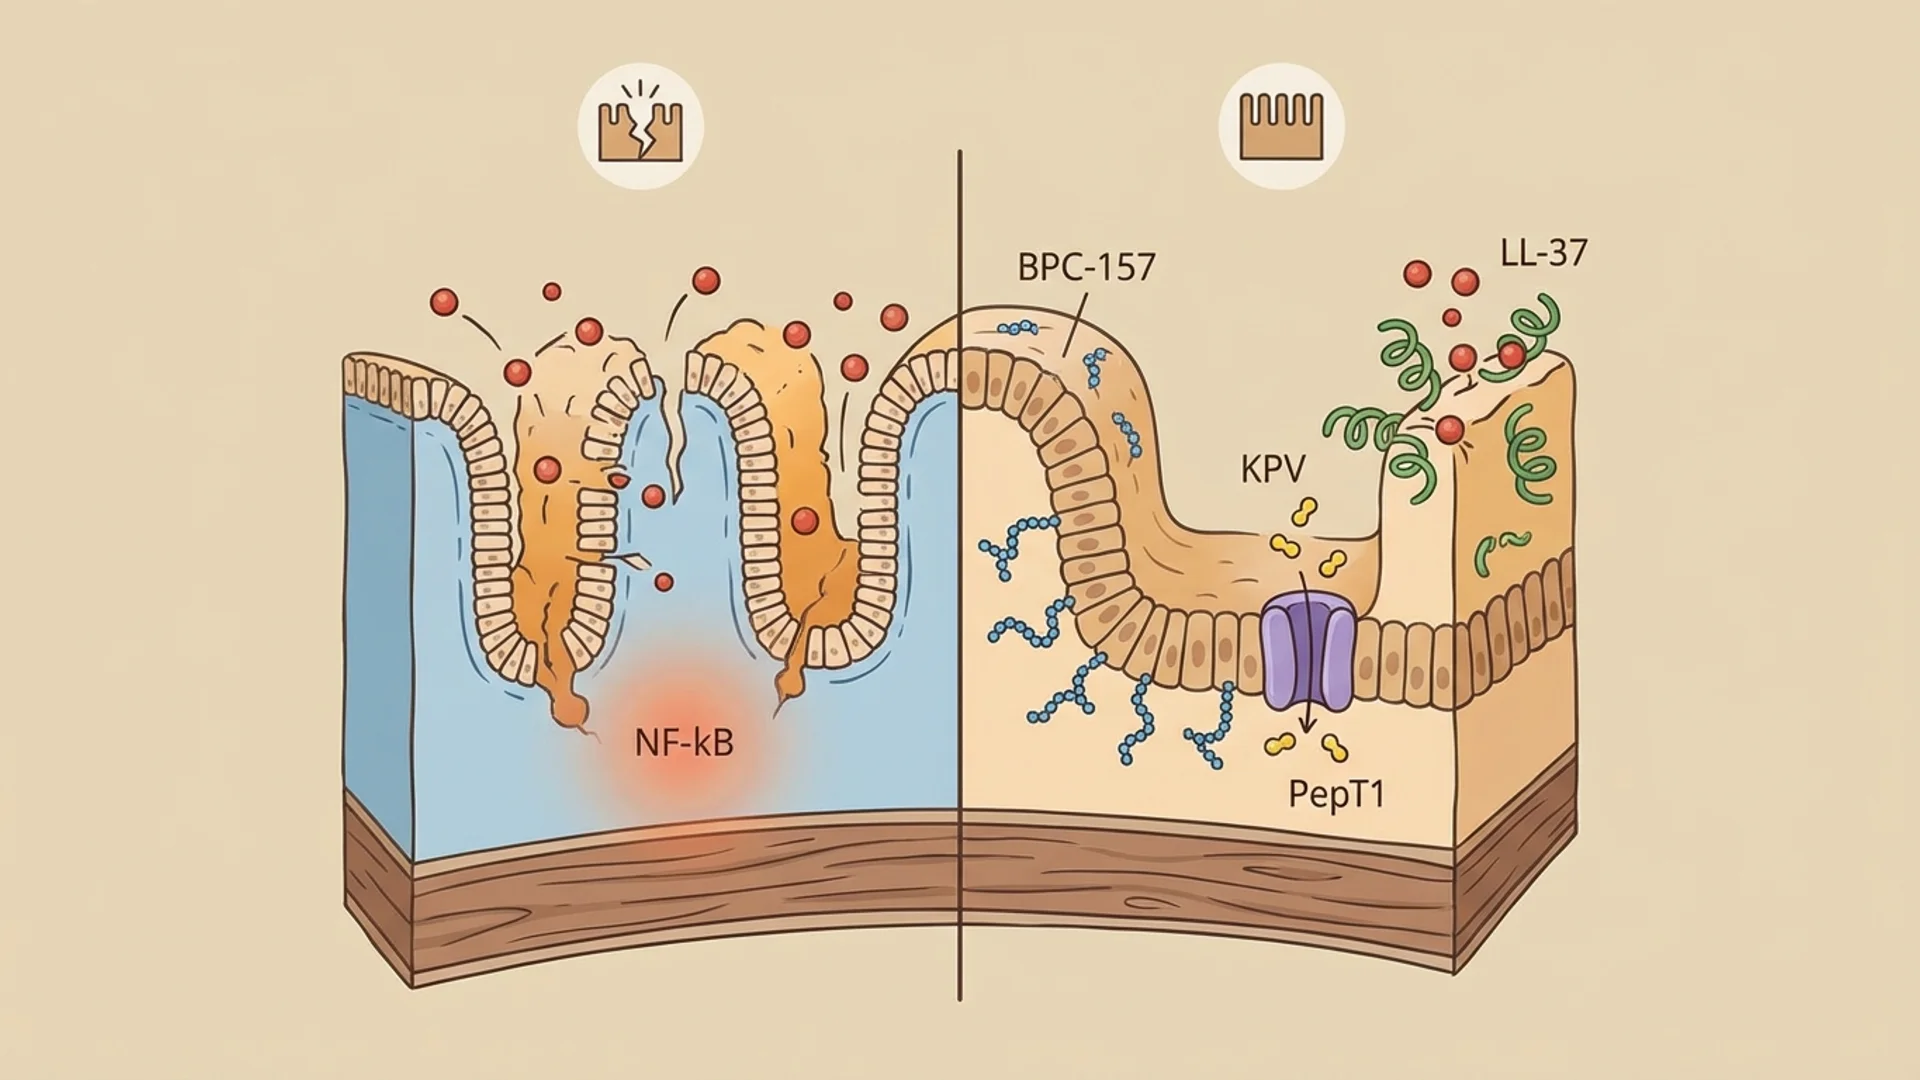
- KPV targets intestinal inflammation through NF-kB inhibition with preferential absorption in inflamed tissue
- Peptides work best when the underlying causes of gut dysfunction are addressed simultaneously
- This protocol is a clinical framework based on preclinical data and clinical observation, not RCT-validated guidelines
Gastrointestinal dysfunction is one of the most common presenting complaints in my practice. Whether it manifests as inflammatory bowel disease, post-infectious irritable bowel syndrome, antibiotic-associated gut damage, or the vague but real syndrome of increased intestinal permeability (“leaky gut”), compromised gut function undermines systemic health in ways that extend far beyond digestive symptoms.
The gut is also, arguably, the organ system for which peptide therapy has the strongest mechanistic rationale. BPC-157 was derived from gastric juice. KPV is preferentially transported into inflamed intestinal tissue. LL-37 is part of the mucosal immune defense. These are not molecules being repurposed for gut applications — they have direct biological connections to gastrointestinal function.
This protocol describes the phased approach I walk people through when I coach them on gut healing (mostly US patients), and where these peptides fit in the evidence. I want to be clear that while the mechanistic rationale is strong and the preclinical data is compelling, we are working primarily with animal study data. Controlled human trials for these specific applications and combinations have not been published.
Who This Protocol Is For
- Patients with documented intestinal inflammation (IBD, microscopic colitis)
- Patients with increased intestinal permeability confirmed by testing (lactulose/mannitol, zonulin)
- Patients with post-infectious irritable bowel syndrome
- Patients with NSAID-induced gastropathy
- Patients recovering from gastrointestinal surgery
- Patients with antibiotic-associated gut damage
Who Should NOT Follow This Protocol Without Medical Supervision
- Patients with undiagnosed gastrointestinal symptoms (rule out serious pathology first)
- Patients with active gastrointestinal malignancy
- Patients with active gastrointestinal infection (address infection before immunomodulation)
- Pregnant or lactating women
- Patients on immunosuppressive therapy (consult prescribing physician)
Phase 1: Remove and Repair Foundations (Weeks 1-2)
Goal
Identify and remove gut-damaging factors. Establish foundational nutritional support for gut healing.
Actions
Diagnostic Assessment:
- Comprehensive stool analysis (microbiome composition, inflammatory markers, digestive function)
- Intestinal permeability testing (lactulose/mannitol ratio or zonulin levels)
- Food sensitivity testing (IgG panel; acknowledging the limitations of these tests)
- Celiac screening if not previously done
- Inflammatory markers (fecal calprotectin, CRP)
Remove Gut-Damaging Factors:
- Discontinue NSAIDs if possible (consult prescribing physician)
- Eliminate identified food triggers
- Reduce or eliminate alcohol
- Assess and address chronic medication effects on gut mucosa
Foundational Supplements:
Supplement Dose Timing Evidence Level Purpose
Zinc carnosine 75 mg twice daily With meals RCTs Mucosal protection, ulcer healing
Vitamin A 10,000 IU/day With meals (fat) Controlled studies Mucosal immune function, epithelial integrity
evidence-based probiotic therapys (multi-strain, 50+ billion CFU) Per label With meals Meta-analyses Microbiome support
Bone broth or collagen peptides 10-20 g/day Any time Traditional/clinical observation Glycine, proline for gut lining repair
Dietary:
- Elimination diet or low-FODMAP diet (depending on presentation)
- Anti-inflammatory whole foods emphasis
- Adequate protein intake (1.2-1.5 g/kg/day)
- Bone broth daily
What to Expect
Some patients notice improvement in digestive symptoms within the first 1-2 weeks from dietary changes and foundational supplements alone. Others may experience temporary worsening as the microbiome adjusts to dietary changes. This phase is the foundation for everything that follows.
Phase 2: Peptide Therapy — Anti-Inflammatory (Weeks 3-10)
Goal
Reduce intestinal inflammation and begin mucosal repair using targeted peptide therapy.
Actions
For informational purposes only — this summarises doses used in research and practice; it is not a prescription or individual medical advice.
Peptide Protocol:
| Peptide | Dose | Route | Frequency | Duration | Evidence Level | Purpose |
|---|---|---|---|---|---|---|
| KPV | 200-500 mcg | Oral (capsule) | Once daily | 8 weeks | Animal studies (colitis models) | NF-kB inhibition, targeted anti-inflammatory in inflamed mucosa |
Notes on Administration:
- BPC-157 oral administration is supported by its stability in gastric juice. For GI applications, oral is the preferred route because it delivers the peptide directly to the intestinal mucosa.
- KPV oral administration exploits the PepT1 transporter, which is upregulated in inflamed intestinal tissue. This provides preferential delivery to the areas that need it most.
- For patients with primarily lower GI involvement (distal colitis, rectal inflammation), compounded KPV suppositories (500 mcg-1 mg) may provide more direct delivery.
Neither BPC-157 nor KPV has a published controlled human trial in gut disease, and the FDA lists both among compounding substances that may present significant safety risks. More detail: BPC-157 Dosage Guide and KPV for Gut Inflammation.
Continue:
- All foundational supplements from Phase 1
- Dietary modifications
Monitoring (Week 6):
- Clinical symptom assessment (stool frequency, consistency, pain, bloating)
- Fecal calprotectin (if elevated at baseline)
- Adjust dosing based on response
What to Expect
When improvement comes in this phase, it is usually driven by removing gut-damaging factors, the dietary changes, and treatment of any underlying disease. Reduced abdominal pain, improved stool consistency, and decreased bloating are the changes to watch for, along with less reactivity to foods that previously caused symptoms.
Phase 3: Mucosal Immune Support (Weeks 6-10, overlapping with Phase 2)
Goal
For patients with evidence of mucosal immune dysfunction or recurrent infections, add LL-37 for antimicrobial and immune support.
Actions
Indications for adding LL-37:
- Documented or suspected SIBO (small intestinal bacterial overgrowth)
- Recurrent gastrointestinal infections
- Post-infectious IBS with evidence of persistent mucosal immune activation
- chronic Lyme disease treatment disease with gastrointestinal involvement
Not all patients need LL-37. For straightforward gut barrier dysfunction without infectious or immune components, BPC-157 and KPV are sufficient. LL-37 has no trials in SIBO or gut infection and is on the FDA’s compounding safety-risk list, and SIBO and recurrent gastrointestinal infections have established diagnostic and treatment pathways that come first.
What to Expect
Patients receiving LL-37 may experience mild flu-like symptoms in the first few days as innate immune activation occurs. This is typically self-limiting. Improvements in symptoms related to SIBO or recurrent infections may become apparent within 2-3 weeks.
Phase 4: Consolidation and Microbiome Restoration (Weeks 11-16)
Goal
Consolidate mucosal healing gains and restore a healthy microbiome for long-term gut health.
Actions
Microbiome Restoration:
Supplement Dose Timing Evidence Level Purpose
Prebiotic fiber (gradually increase) 5-10 g/day With meals Controlled studies Feed beneficial bacteria
Fermented foods Daily portions With meals Observational Diverse microbial exposure
Short-chain fatty acid support (butyrate) 300-600 mg With meals Controlled studies Colonocyte fuel, anti-inflammatory
Dietary Reintroduction:
- Gradual reintroduction of eliminated foods (one every 3-4 days)
- Monitor for symptom recurrence
- Build toward a diverse, whole-foods anti-inflammatory diet
What to Expect
By this phase, most responding patients have experienced significant improvement in digestive symptoms. The focus shifts from acute healing to establishing a sustainable gut environment. Some patients find that foods they previously could not tolerate can be reintroduced successfully.
When to Seek Medical Help
- Blood in stool (new onset or worsening)
- Severe abdominal pain not explained by the treatment protocol
- Unexplained weight loss exceeding 5% of body weight
- Fever during treatment (could indicate infection)
- Signs of allergic reaction to any peptide (hives, swelling, difficulty breathing)
- Symptoms worsening progressively rather than fluctuating and improving
- New symptoms not previously present
Monitoring and Assessment
- Fecal calprotectin at baseline, week 6, and week 14 (for patients with inflammatory bowel disease)
- Intestinal permeability testing at baseline and week 14 (for patients with confirmed increased permeability)
- Stool analysis at baseline and week 14
- Clinical symptom scoring at each visit
- Dietary diary throughout the protocol
Long-Term Maintenance
After completing the protocol:
- Maintain diverse, anti-inflammatory diet
- Continue probiotics and prebiotic fiber long-term
- Zinc carnosine and L-glutamine can be continued at maintenance doses
- Repeat BPC-157 course (4 weeks) if symptoms recur
- Annual stool analysis to monitor microbiome health
- Address new gut-damaging exposures promptly (stress, medication changes, infections)
Clinical Perspective
The gut is where the mechanistic case for peptides is strongest. BPC-157 was derived from gastric juice, has extensive preclinical data for GI protection and healing, and is stable in gastric acid. KPV’s NF-kB inhibition and PepT1-mediated uptake in inflamed tissue are an elegant rationale for targeted anti-inflammatory delivery. But a strong mechanism is not the same as a tested treatment: neither peptide has a controlled human trial in gut disease, the doses above come from clinical practice rather than dose-finding trials, the BPC-157 and KPV combination has never been formally studied, and both are flagged by the FDA as compounding safety risks.
I want to be clear about what this protocol is not: it is not a replacement for appropriate medical management of inflammatory bowel disease. Patients with moderate to severe IBD need gastroenterological care, and peptide therapy is an adjunct to — not a substitute for — evidence-based IBD treatment. For patients with milder gut dysfunction, gut barrier issues, or post-infectious IBS, this protocol may be appropriate as a primary intervention under physician supervision.
The most important point is that the foundations do the heavy lifting. Patients who address the underlying causes of gut dysfunction — dietary triggers, medication effects, stress, sleep quality — respond significantly better than those who rely on peptides while maintaining the habits that damaged their gut in the first place. The foundation matters more than the peptides.

References
- Sikiric P, et al. “Stable gastric pentadecapeptide BPC 157 in trials for inflammatory bowel disease.” Ann N Y Acad Sci. 2006;1070:324-340.
- Sikiric P, et al. “Toxicity by NSAIDs. Counteraction by stable gastric pentadecapeptide BPC 157.” Curr Pharm Des. 2013;19(1):76-83.
- Dalmasso G, et al. “PepT1-mediated tripeptide KPV uptake reduces intestinal inflammation.” Gastroenterology. 2008;134(1):166-178.
- Kannengiesser K, et al. “Melanocortin-derived tripeptide KPV has anti-inflammatory potential in murine models of IBD.” Inflamm Bowel Dis. 2008;14(3):324-331.
- Vandamme D, et al. “A comprehensive summary of LL-37, the factotum human cathelicidin peptide.” Cell Immunol. 2012;280(1):22-35.
- Rao R, Samak G. “Role of glutamine in protection of intestinal epithelial tight junctions.” J Epithelial Biol Pharmacol. 2012;5(Suppl 1-M7):47-54.
- Mahmood A, et al. “Zinc carnosine, a health food supplement that stabilises small bowel integrity.” Gut. 2007;56(2):168-175.
Disclaimer: This protocol is provided for educational purposes and reflects one physician’s clinical approach. It is not a substitute for individualized medical care. Gastrointestinal conditions require proper diagnosis before treatment. Consult a qualified physician before beginning any supplement or peptide protocol.



